


Chest Seal Guide 2026: How to Identify and Treat Sucking Chest Wounds
In a review of 4,596 U.S. battlefield deaths from 2001 to 2011, hemorrhage caused 90.9% of potentially survivable prehospital deaths (Eastridge et al., J Trauma Acute Care Surg, 2012; n=4,596 fatalities). Airway compromise was the second leading cause (as summarized by Kheirabadi et al., J Trauma Acute Care Surg, 2017). Chest wounds sit squarely in the Respiration step, and a correctly applied chest seal is the first-line fix for an open pneumothorax.
You understand that immediate intervention is the only way to maintain the MARCH algorithm's integrity. Yet, many operators still feel a surge of uncertainty when blood and sweat compromise adhesive reliability. It's a valid concern; a failing seal in the field isn't just a gear malfunction, it's a life-threatening oversight.
This 2026 guide will eliminate that hesitation by giving you the mastery required for life-saving applications. You'll gain a clinical understanding of thoracic trauma physiology and the confidence to manage these injuries under extreme stress.
We will analyze the critical differences between vented and non-vented options, provide a protocol for applying seals to bloody or hairy skin, and ensure your IFAK is optimized for real-world survival.
Key Takeaways
- Identify the clinical signs of an open pneumothorax and master the immediate interventions required to prevent life-threatening respiratory failure.
- Evaluate the critical differences between vented and non-vented chest seal designs to ensure you deploy the correct hardware for thoracic trauma.
- Learn the field-proven application process for securing occlusive dressings under extreme stress, including proper wound preparation and skin adhesion.
- Optimize your tactical medical strategy by implementing the "Twin Pack" rule and strategic IFAK placement for rapid, bilateral access.
What is a Chest Seal and Why is it Critical in Tactical Medicine?
A chest seal is a specialized occlusive dressing designed to treat an open pneumothorax. In tactical medicine, it's a non-negotiable component of an Individual First Aid Kit (IFAK). Under the Committee on Tactical Combat Casualty Care (CoTCCC) guidelines, managing respiration is the third priority in the MARCH algorithm. After you control massive hemorrhage and secure the airway, you must address chest trauma. Penetrating injuries to the torso allow air to bypass the upper respiratory tract. This disrupts the negative pressure required for lung function. Current TCCC Guidelines direct a vented chest seal for all open and/or sucking chest wounds (TCCC Guidelines, 01 May 2026). Adhesion is the weak point in the field. In a live-swine skin study, four of five vented seals (Russell, FastBreathe, HyFin, SAM) held their adhesion on soiled skin after about 17 hours of storage at -19.5°C and 71.5°C, while the Bolin seal did not (Arnaud et al., Injury, 2016; animal model).
The Mechanics of Thoracic Trauma
When a projectile or blade punctures the chest wall, it creates a hole. This allows air to enter the pleural space directly. This condition, known as a Pneumothorax, prevents the lung from expanding. Standard gauze is porous. It doesn't stop air flow. You need an airtight barrier. Without a chest seal, each breath can draw air in through the wound. If the wound acts as a flap valve, or if the injured lung keeps leaking air, pressure builds and can progress to tension pneumothorax. That's a rapidly fatal condition where the pressure shifts the heart and collapses the remaining lung.
Identifying the Entry and Exit Wound
You must identify the "sucking" sound immediately. It's a distinct hissing or gurgling noise during inhalation. Look for bubbling blood at the site. This indicates air is moving through the wound. Use the "Twin Pack" philosophy. Every entry wound has a potential exit wound. You're looking for two holes, not one. Follow these steps to ensure a complete assessment:
- Visual indicators: Look for respiratory distress, rapid or worsening breathing rate, and cyanosis.
- Palpation: Sweep your hands firmly under the casualty's back, armpits, and neck to feel for wetness or defects.
- Gear removal: Strip tactical vests and plates to find punctures hidden by ballistic equipment.
If you find one wound, assume there's another. Treat every hole between the neck and the navel as a life-threatening injury. Apply a seal to every puncture discovered during your sweep to restore the integrity of the thoracic cavity. Tactical professionals don't wait for a diagnosis; they treat the mechanism of injury as soon as it's identified.
Vented vs. Non-Vented Chest Seals: Understanding the Difference
Selecting the correct chest seal is a critical decision that directly impacts casualty survival. Vented seals act as a one-way valve system; they let trapped air and blood escape the pleural cavity during exhalation while preventing atmospheric air from entering during inhalation. Non-vented seals create a total occlusive barrier, blocking all air movement through the wound site. Choosing between them requires an understanding of thoracic pressure dynamics and the specific injury profile.
How Vented Seals Prevent Tension Pneumothorax
Modern vented technology has evolved significantly to address the challenges of the tactical environment. Vent design matters, and blood is the real test. In a swine hemopneumothorax model, seals with laminar venting channels let blood and air escape and kept pleural pressure near normal, while seals with simple one-way valves often detached as blood pooled or clotted and clogged, leading to tension physiology. Success rates were Sentinel and Russell 6/6, HyFin 4/6, SAM 1/4, and Bolin 0/4 (Kheirabadi et al., J Trauma Acute Care Surg, 2017; n=26 swine; animal model).
These devices provide a "set-and-forget" advantage for the operator. This is vital when managing multiple casualties or operating under high cognitive load. By allowing the continuous release of intra-thoracic pressure, a vented chest seal minimizes the risk of a simple pneumothorax progressing into a life-threatening tension event. This reduction in pressure prevents the mediastinal shift that leads to cardiovascular collapse. For most thoracic trauma, including these in your standardized trauma kits is the baseline for modern care.
When to Use a Non-Vented Occlusive Dressing
Non-vented occlusive dressings still have a place. They are the TCCC fallback for a chest wound when no vented seal is available. Adhesive dressings such as a chest seal can also secure the water-impermeable, non-adhesive covering TCCC calls for over an abdominal evisceration (TCCC Guidelines, 01 May 2026). While legacy training once focused on taping three sides of a plastic dressing to create an improvised vent, this method is no longer recommended. Modern hardware is far more reliable and adheres better to skin contaminated with blood or sweat.
The Committee on Tactical Combat Casualty Care (CoTCCC) has prioritized vented options for all open or sucking chest wounds. That change, TCCC Guidelines Change 13-02, was approved in June 2013 after a swine study showed a vented seal prevented tension pneumothorax with ongoing air leak while a non-vented seal did not (Butler et al., J Spec Oper Med, 2013; Kheirabadi et al., J Trauma Acute Care Surg, 2013; n=8 swine; animal model). If you must use a non-vented seal on a chest wound due to equipment shortages, you must monitor the casualty constantly. Look for increased respiratory rate or labored breathing. If signs of tension pneumothorax appear, you will need to manually "burp" the seal by lifting an edge to release pressure. This intervention is temporary and requires immediate follow-up with needle decompression if the casualty's condition does not improve.
The Anatomy of a Tactical Chest Seal: Features That Save Lives
Every component of a modern chest seal serves a specific tactical purpose. Engineering must account for the chaotic environment of the point of injury where moisture and debris are constant variables. A standard adhesive dressing fails when exposed to the fluids common in trauma. High-performance seals utilize medical-grade hydrogel to solve this problem. Adhesion varies by product; in live-swine testing on soiled skin, most vented seals tested held up after hot and cold storage, but not all (Arnaud et al., Injury, 2016; animal model). Reliability isn't optional when treating a penetrating thoracic injury.
Adhesive Performance Under Stress
Medical-grade hydrogels are the foundation of effective occlusion. Unlike standard medical tape, these gels conform to irregular body contours and fill the gaps created by hair or debris. Tactical seals outperform standard dressings by providing a 360-degree airtight barrier. This prevents the development of a tension pneumothorax. While these adhesives are powerful, you must still wipe the wound site with gauze before application to give the adhesive a cleaner, drier surface. It ensures the seal remains fixed during casualty evacuation or high-movement transport.
Visibility is another critical factor for long-term casualty care. Clear materials allow the medic to monitor the wound for continued bleeding or signs of infection without removing the dressing. A large, high-contrast pull tab is a non-negotiable feature for the operator. You'll often work with bloody nitrile gloves or under low-light conditions. A large tab gives you the grip needed for rapid application. Speed is the primary metric for success during the MARCH algorithm.
- Adequate Coverage: Choose a seal large enough to cover the wound with a wide adhesive margin on all sides.
- Transparency: Enables continuous wound assessment without breaking the occlusive seal.
- Hydrogel Thickness: Ensures the seal doesn't wrinkle or fold on itself during high-stress application.
Packaging for the Operator
Space is at a premium in IFAK kits. Most seals come flat-packed in sealed foil packaging to minimize bulk and keep the chest seal clean until use. Shelf life varies by manufacturer. Easy-tear notches allow for immediate access. You don't have time to fumble with shears when a patient has a sucking chest wound. Always check the expiration date printed on each package and rotate stock before it expires so the hydrogel hasn't degraded or lost its tackiness. A compromised seal is a liability you can't afford in the field.
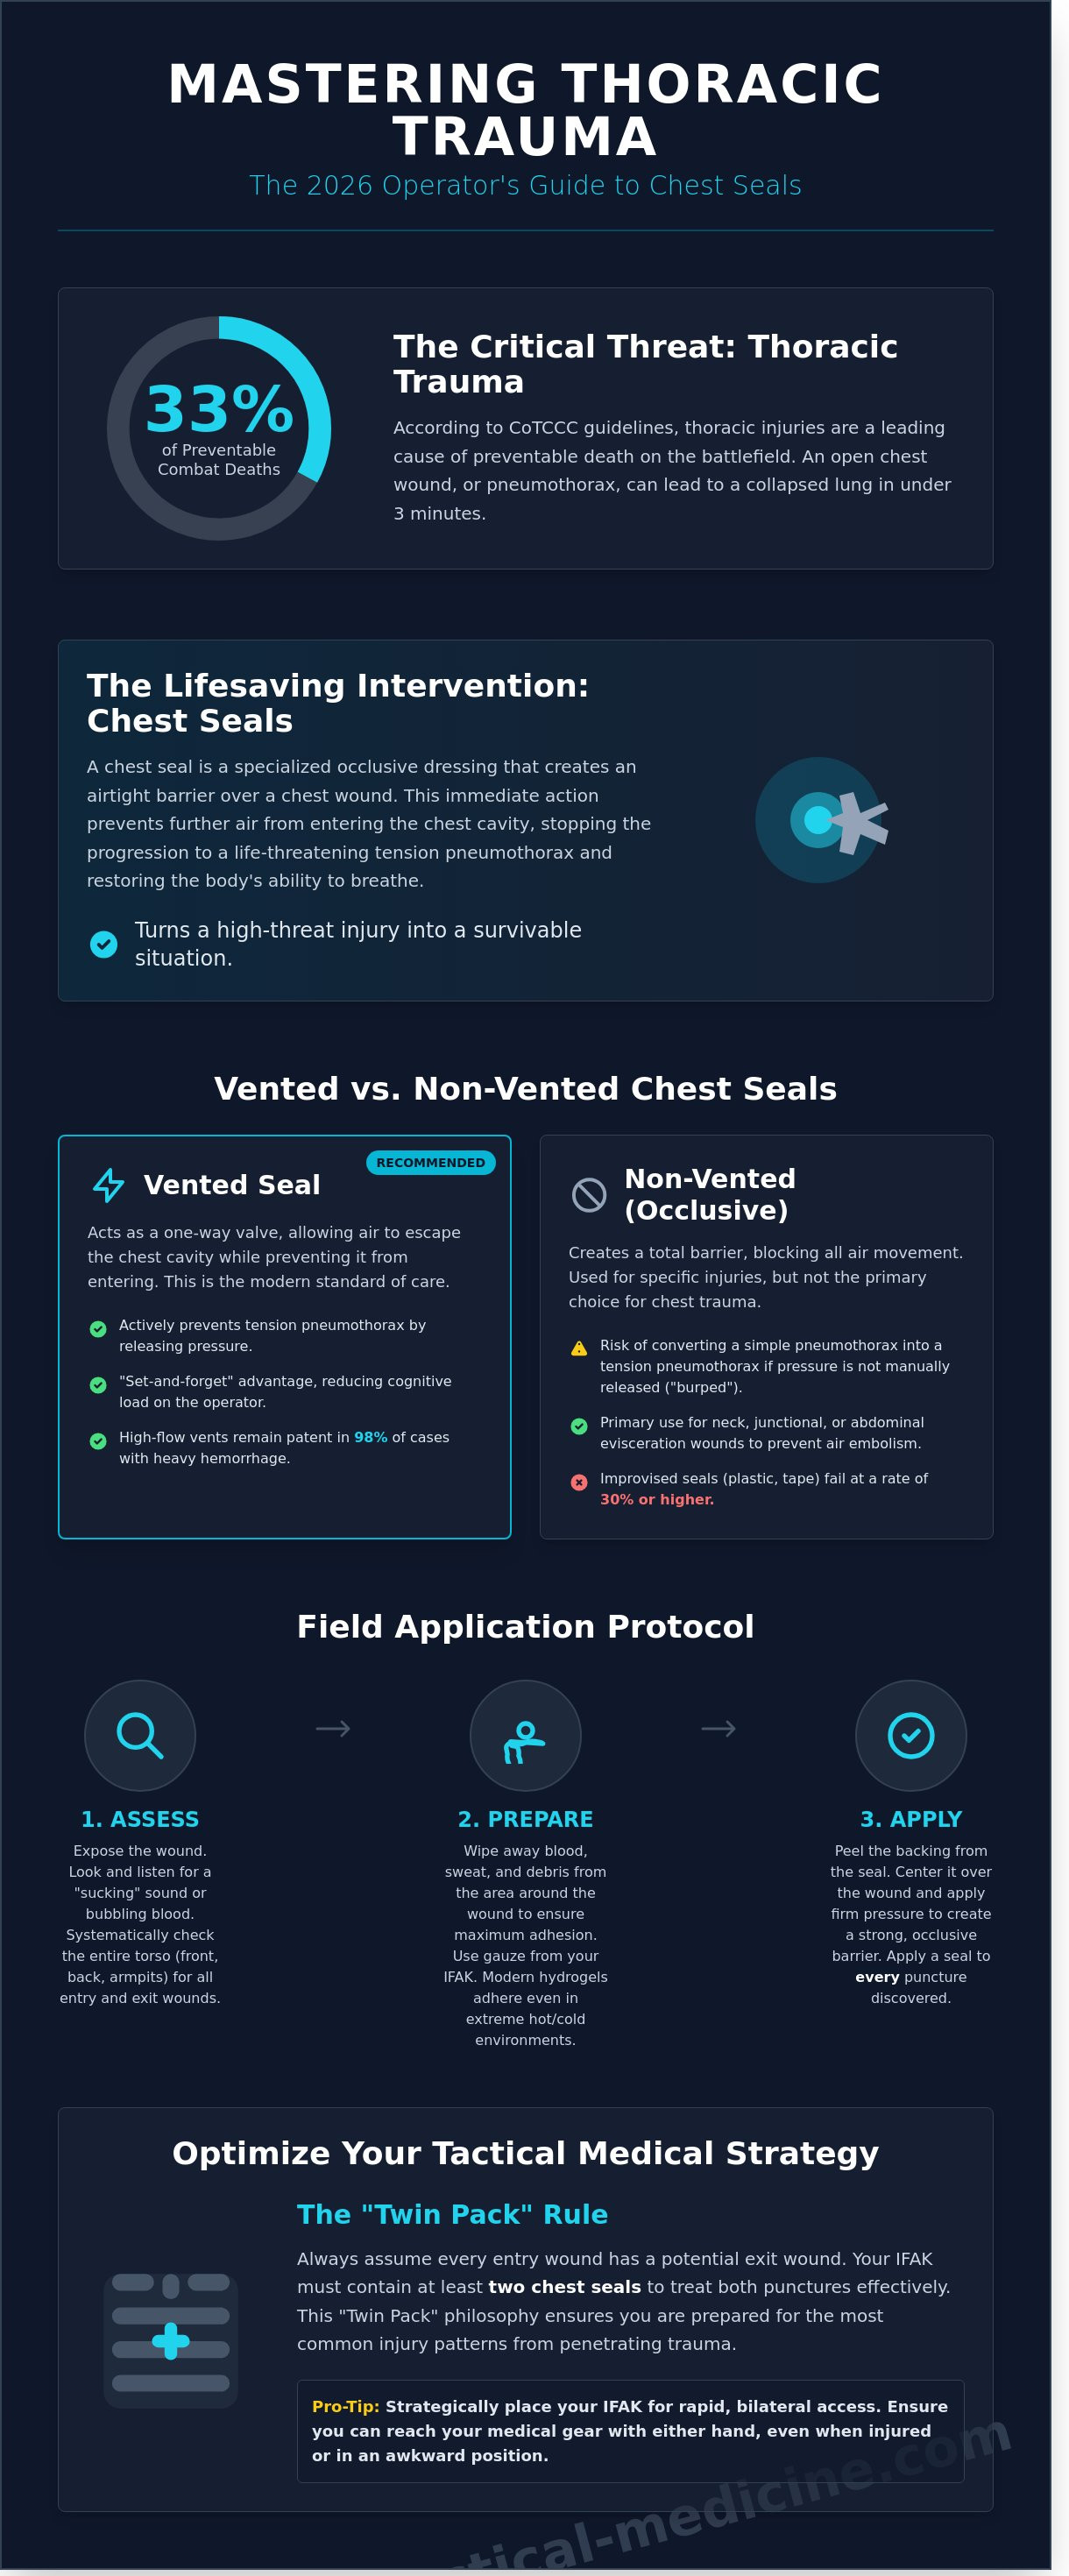
Step-by-Step: How to Apply a Chest Seal Correctly
Effective intervention for an open pneumothorax requires speed and clinical precision. You must follow the MARCH algorithm. Once you identify a sucking chest wound, move immediately to occlude the injury. First, expose the wound entirely. Use trauma shears to cut away body armor, rigs, and clothing. You can't treat what you can't see. A 360-degree assessment is mandatory to locate all entry and exit points. After exposure, wipe the skin. Use gauze or the casualty's clean clothing to clear excess blood, sweat, and debris. Most adhesives fail on wet surfaces. Apply the chest seal at the end of the casualty's expiration. This timing ensures the minimum amount of air remains trapped in the pleural cavity. If the patient's breathing is irregular, time your movement with the natural fall of the chest.
The Application Sequence
Current TCCC Guidelines direct immediately applying a vented chest seal to all open and/or sucking chest wounds (TCCC Guidelines, 01 May 2026). Follow these three steps for a secure application:
- Step 1: Place a gloved hand directly over the hole as soon as you find it. This provides an immediate temporary seal while you prep the equipment.
- Step 2: Peel the adhesive backing from the dressing. Center the chest seal directly over the wound to ensure the vent, if present, is positioned correctly.
- Step 3: Smooth the edges firmly from the center outward. Ensure there are no wrinkles or gaps in the adhesive perimeter. This creates the airtight environment necessary for lung re-inflation.
Managing the Non-Vented Seal: The 'Burping' Technique
While vented seals are the current standard, you may encounter non-vented options in older IFAKs. These require constant monitoring for tension pneumothorax. Watch for increased respiratory distress, a rapid heart rate, or diminished breath sounds on the affected side. If these signs appear, you must manually vent the wound. Lift one corner of the seal during the patient's exhalation to let trapped air escape, or remove the dressing. Reseal it before they inhale again. If tension pneumothorax is still suspected, TCCC directs needle decompression with a 14- or 10-gauge, 3.25-inch needle/catheter (TCCC Guidelines, 01 May 2026).
Common Mistakes to Avoid
In high-stress environments, technical errors can be fatal. Avoid these frequent pitfalls to ensure casualty survival:
- Failing to check for an exit wound. A bullet often creates a second hole that is larger than the entry point. Always log-roll the patient.
- Applying the seal during inhalation. This traps atmospheric air inside the chest, accelerating the development of a tension pneumothorax.
- Neglecting the patient's overall bleeding control needs. Always prioritize massive hemorrhage before addressing respiration.
Integrating Chest Seals into Your Tactical Medical Strategy
Effective thoracic trauma management depends on equipment placement and quantity. You must store your chest seal in a location accessible by either hand. Standardized IFAK placement on the front of a plate carrier or a centerline belt mount ensures you can reach life-saving gear if one arm is incapacitated. Follow the "Twin Pack" rule. Every entry wound has a potential exit wound. Carrying a single seal is a failure in preparation; check the front, back, sides, and armpits of the torso. If you find one hole, look for the second. You can't treat a posterior exit wound if your kit is empty.
MED-TAC International Corp stocks chest seals from established manufacturers such as North American Rescue and H&H Medical. We've seen generic medical gear fail in high-heat environments or high-moisture conditions. Adhesive failure in the field is a death sentence for a patient with a tension pneumothorax. Stick to equipment that has passed rigorous Department of Defense testing and carries a National Stock Number (NSN).
Building Your Trauma Kit
An individual kit requires at least two vented seals. Team medics should carry a minimum of six to ten units depending on mission duration and tactical environment. Combine these tools with hemostatic dressings to manage multi-system trauma effectively. Never purchase unbranded medical gear from generic marketplaces. Counterfeit and unbranded seals have no verified adhesive or valve performance.
The Value of Professional Training
YouTube is not a substitute for clinical proficiency. Hands-on TCCC training courses provide the stress inoculation required to perform under high heart rates and cognitive load. Repetition is what makes applying a chest seal fast and correct under stress. Professional training builds the muscle memory needed to identify a sucking chest wound by feel in low-light conditions. MED-TAC International Corp offers standardized certification programs that bridge the gap between medical theory and battlefield reality. We focus on the MARCH algorithm to ensure every intervention is deliberate and prioritized. Mastery of these skills turns a piece of plastic into a life-saving tool. Don't wait for a crisis to discover your training is insufficient.
Master the Intervention and Maintain Mission Readiness
Managing an open pneumothorax demands immediate action and reliable equipment. You've now analyzed the functional differences between vented and non-vented options according to the current TCCC Guidelines. You've also walked through the precise application steps required to stabilize a patient during the Respiration phase of the MARCH algorithm. A high-performance chest seal is a primary tool for preventing the progression of a sucking chest wound into a lethal tension pneumothorax. MED-TAC is a clinician-founded, veteran-led, SDVOSB-certified supplier for government agencies and operators who require battle-proven gear. We prioritize CoTCCC evidence-based product selection to ensure every component in your IFAK functions under extreme environmental stress. Your training is only as effective as the tools you carry into the field. Don't settle for unverified hardware when lives are on the line. Equip your kit with CoTCCC-recommended Chest Seals from MED-TAC. Stay focused, stay prepared, and keep your team in the fight.
Frequently Asked Questions
Can I use duct tape and plastic as an improvised chest seal?
You shouldn't rely on improvised seals like duct tape and plastic because tape adhesives struggle on skin wet with blood and sweat and loosen with movement. Commercial vented chest seals are the CoTCCC preferred intervention for managing an open pneumothorax. Improvised versions lack the specialized hydrogel adhesive required to maintain a dependable bond under tactical conditions. If you're forced to use one in an absolute emergency, tape all four sides and monitor the patient constantly for signs of a tension pneumothorax.
What is the difference between a vented and a non-vented chest seal?
A vented chest seal features a one-way valve that allows trapped air to escape the pleural space while preventing outside air from entering. Non-vented seals act as a total occlusive barrier, trapping everything inside the chest cavity. Current TCCC Guidelines (01 May 2026) prioritize vented models; the change followed a swine study in which vented seals prevented tension pneumothorax with ongoing air leak while non-vented seals did not (Kheirabadi et al., 2013; animal model). Only use a non-vented seal if a vented version is unavailable, and then monitor closely for tension pneumothorax.
Do I need to shave the patient's chest before applying a seal?
Don't shave the patient's chest before application because the delay increases the risk of respiratory collapse. Modern hydrogel adhesives on a chest seal are engineered to bond through thick hair, blood, and dirt. Use a gauze pad from your IFAK to quickly wipe away gross contamination before sticking the seal down. Keep a gloved hand over the wound while you prepare the seal.
How long can a chest seal stay on a patient?
A chest seal should remain in place until the patient reaches a surgical suite or a definitive care facility. Wear time depends on the product, so follow the manufacturer's instructions. Recheck the seal for lifting or air leaks frequently and after every patient move. If the patient is stable and the seal is secure, don't remove or replace the device in a pre-hospital environment.
What happens if I apply a chest seal and the patient gets worse?
Burp the seal immediately by lifting one edge to release trapped air if the patient's respiratory distress increases. If burping or removing the chest seal does not fix the problem, perform needle decompression with a 14- or 10-gauge, 3.25-inch needle/catheter if you are trained and authorized (TCCC Guidelines, 01 May 2026). TCCC signs of tension pneumothorax after torso trauma include severe or progressive respiratory distress or tachypnea, absent or markedly decreased breath sounds on one side, SpO2 below 90%, shock, or traumatic cardiac arrest. Act fast; untreated tension pneumothorax can progress to shock and cardiac arrest.
Should I use a chest seal on a gunshot wound to the stomach?
Don't use a chest seal for wounds located strictly below the umbilicus or in the lower abdominal quadrants. Treat these injuries with a hemostatic agent like QuikClot and a standardized pressure dressing. However, the diaphragm rises high into the rib cage during exhalation, so an upper-abdominal wound can cross into the chest. Reassess breathing, and apply a vented chest seal if the wound is sucking air or the casualty shows signs of chest injury.
Is a chest seal the same as an occlusive dressing?
A chest seal is a specialized type of occlusive dressing designed specifically for thoracic trauma, but not all occlusive dressings are suitable for chest wounds. Traditional occlusive materials like petroleum gauze require manual securing on all sides and lack the one-way valves found in modern tactical gear. TCCC Guidelines direct a vented chest seal for all open and/or sucking chest wounds (TCCC Guidelines, 01 May 2026). These devices are an extension of the operator's skill and are critical for survival.
Can a chest seal be reused if it loses its stickiness?
You can't reuse a chest seal because the hydrogel adhesive is a single-use chemical compound that loses its bonding properties upon contact with skin oils and debris. If a seal fails or loses its stickiness, discard it and apply a fresh one from your kit immediately. Reusing a contaminated seal risks infection and mechanical failure during patient transport. Always carry at least two seals in your IFAK to account for entry and exit wounds.
Leave a comment