


Traction Splint: The Operator’s Guide to Femur Fracture Management
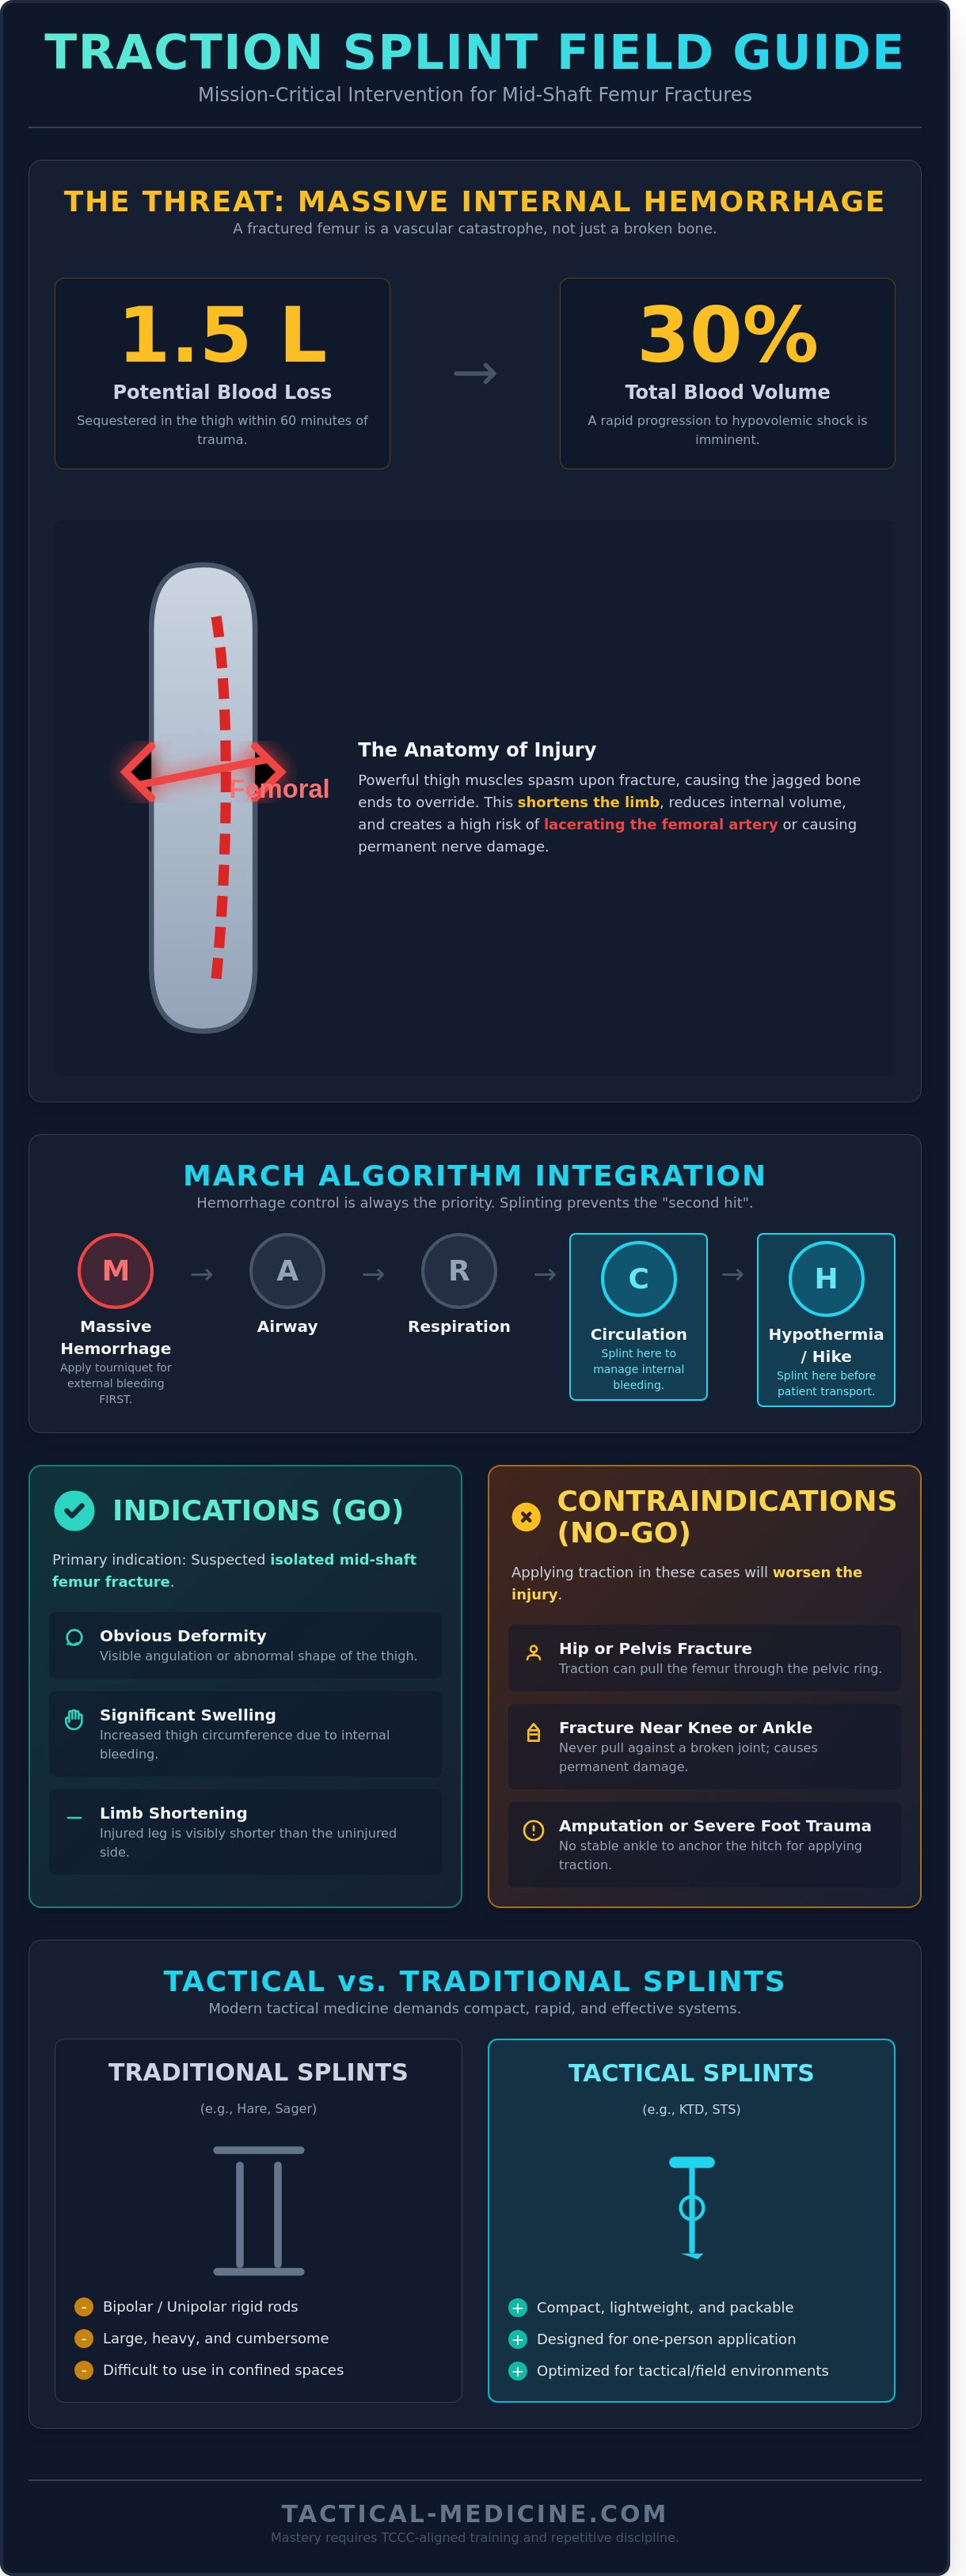
A femur fracture can be expected to cost the patient about 1 to 1.5 liters of blood into the thigh, up to 30% of normal blood volume (Davis et al., EMS Traction Splint, StatPearls, 2023). In a high-threat environment, this injury isn't merely an orthopedic concern; it's a life-threatening internal hemorrhage that directly challenges your MARCH algorithm priorities. You recognize that fumbling with complex hardware during a casualty evacuation increases the risk of shock and permanent neurovascular damage. Deploying a traction splint is a critical intervention that demands clinical precision and tactical speed.
You've likely faced the dilemma of balancing limited space in a mission-specific medical bag against the need for rugged, dependable equipment. This guide provides the expertise you need to master the indications, selection, and field application of modern splinting systems. We'll analyze TCCC-aligned protocols, offer a step-by-step proficiency breakdown for one-man application, and identify the field-proven devices that ensure your patient survives the flight or the drive to the next level of care.
Key Takeaways
- Identify the life-threatening hemorrhage risks associated with mid-shaft femur fractures and why immediate stabilization is non-negotiable.
- Evaluate the critical differences between bipolar, unipolar, and tactical traction splint designs to ensure your loadout matches your operational environment.
- Master the visual cues for deployment and learn to recognize contraindications that could compromise patient outcomes in high-stress scenarios.
- Follow a standardized field protocol for limb realignment, focusing on neurovascular integrity and manual stabilization techniques.
- Bridge the gap between equipment ownership and operational proficiency through TCCC-aligned training and repetitive discipline.
What is a Traction Splint and Why is it Mission-Critical?
A traction splint is a mechanical stabilization device designed to realign mid-shaft femur fractures. In tactical medicine, this tool is mission-critical. A fractured femur isn't just an orthopedic injury; it's a potential vascular catastrophe. Internal blood loss into the thigh is typically about 1 to 1.5 liters, up to 30% of normal blood volume, and the thigh compartments can hold up to 3 liters (Davis et al., StatPearls, 2023). That volume can lead to hypovolemic shock. The device applies constant longitudinal traction to counteract the body's natural response to trauma. It's a standard component of advanced tactical medical kits because it stabilizes the limb and manages internal space during prolonged field care.
The Anatomy of a Femur Fracture
The femur is the largest bone in the human body. It's surrounded by powerful muscle groups that contract immediately upon fracture. This contraction causes a "thigh-shortening" effect where the jagged ends of the bone override each other. The femoral artery lies in close proximity to the bone shaft. Sharp fragments can easily lacerate this artery or damage the femoral nerve. Immobilization is mandatory. By restoring the limb's length, the traction splint is intended to reduce the space available for bleeding in the thigh, relieve pain, and limit further injury from loose bone fragments during transport. High-quality evidence that this improves outcomes is limited (Wood et al., Prehosp Emerg Care, 2003).
Traction Splints in the MARCH Algorithm
Operators must integrate splinting into the MARCH (Massive Hemorrhage, Airway, Respiration, Circulation, Hypothermia) algorithm correctly. In the TCCC Guidelines, "Splint fractures and re-check pulses" is a Tactical Field Care step that follows the MARCH priorities; it is the "S" in MARCH PAWS (TCCC Guidelines, 01 May 2026). You've got to distinguish between immediate life-threats and secondary stabilization. If the fracture is open and bleeding profusely, apply a tourniquet during the "M" phase. Hemorrhage control always precedes the application of a traction splint. Once the site is secure, use the splint to prevent the "second hit" of injury caused by movement during extraction. TCCC directs you to splint fractures and re-check pulses; it does not specify a traction splint model or technique, so follow your device's instructions and local protocol. It's about maintaining the patient's physiological status until they reach a higher level of care.
Indications and Contraindications: When to Deploy Traction
The primary indication for a traction splint is a suspected isolated mid-shaft femur fracture. You'll recognize this injury through several distinct visual cues:
- Obvious deformity or angulation of the thigh.
- Significant swelling and increased circumference of the injured leg.
- Visible shortening of the limb compared to the uninjured side.
These fractures are high-energy injuries. The quadriceps and hamstrings will spasm, pulling jagged bone ends into the surrounding muscle and vasculature. Applying traction isn't just about stabilization; it's critical pain management. By restoring limb length, you neutralize the muscle spasms that cause excruciating agony and internal hemorrhage. Femur fractures carry a risk of hemorrhage, fat embolism, and infection (Davis et al., StatPearls, 2023); early stabilization is intended to limit further injury, although prehospital outcome data for traction splints are limited.
Adhere to the clinical imperative: splint them where they lie. Movement without stabilization risks converting a closed fracture into an open one or injuring nearby vessels.
Absolute Contraindications
Don't apply the device if you suspect a pelvic or hip fracture, an ipsilateral knee injury, or a fracture of the ankle, foot, or lower leg on the same side (Merck Manual Professional, 2025; BC Emergency Health Services protocol PR50). A supracondylar (distal femur) fracture is also a contraindication in the BCEHS protocol. Traction that helps a shaft fracture can harm fractures or ligament injuries distal to it.
Relative Contraindications and Tactical Realities
Assess for lower leg amputations or severe foot trauma. With an ankle-hitch splint, standard traction is not possible without a stable ankle; the manufacturer of the Slishman Traction Splint states its device can still be applied with lower leg or foot amputation. Don't apply a traction splint during Care Under Fire. TCCC places fracture splinting in Tactical Field Care (TCCC Guidelines, 01 May 2026). Reassess distal neurovascular status repeatedly throughout transport. Operators must maintain proficiency with field-proven medical gear to ensure rapid deployment under stress.
Tactical vs. Traditional Traction Splints: A Comparison
The Hare Traction Splint represents the traditional bipolar design. It utilizes two rigid rods to provide stability but creates a footprint too large for modern mobile operations. The Sager unipolar splint improved this by using a single rod, yet it remains cumbersome in confined spaces. Tactical medicine requires a departure from these legacy systems. Operators now prioritize the Kendrick Traction Device (KTD) and the Slishman Traction Splint (STS) for field deployments.
The "proximal hitch" defines the tactical advantage. Legacy splints extend beyond the patient's foot; one EMS protocol sets the Sager about four inches (10 cm) past the heel (BCEHS protocol PR50). That extension can interfere with doors and patient loading in vehicles and aircraft. The STS solves this by keeping all mechanical components proximal to the foot. This design choice ensures the patient fits within the standard litter dimensions, maintaining a streamlined profile during technical extractions.
- Hare (Bipolar): Heavy, requires significant storage, and extends beyond the foot.
- Sager (Unipolar): Allows for bilateral splinting but remains bulky for ruck carry.
- KTD: Lightweight, with a sectional folding pole similar to a tent pole.
- STS: Features a distal point of pull that stays within the patient's footprint.
The Evolution of Compact Design
Traditional Hare splints are too bulky for a medic carrying a standard 3-day assault pack. Tactical variants use telescoping aluminum poles that collapse into a compact package; the manufacturer lists the Slishman Traction Splint Gen2 at 17 ounces. Some units are radiolucent; the STS manufacturer states the splint does not need to be removed for imaging or exam.
Application Speed and Operator Fatigue
Standard protocols for legacy splints often require two providers. One medic maintains manual traction while the second secures the straps. In a high-threat environment, manpower is a luxury. The STS manufacturer states the device can be applied in under 60 seconds with minimal training. Traction is set at the hip with a cord-pull and locking notch rather than a distal ratchet. Whatever the mechanism, recheck tension during long transports. You can evaluate these Tactical Medical Gear options to match your kit to your mission.
How to Apply a Traction Splint: Step-by-Step Field Protocol
Applying a traction splint is a high-stakes intervention that demands technical proficiency. You've got to move with speed while maintaining clinical precision to avoid exacerbating the injury. Follow this five-step protocol to stabilize mid-shaft femur fractures in high-threat environments.
- Step 1: Neurovascular Assessment. Perform a distal Pulse, Motor, and Sensory (PMS) check. Document the presence of a pedal pulse and the patient's ability to feel stimuli. This baseline is critical for identifying vascular compromise during transport.
- Step 2: Manual Traction. An assistant must apply steady, manual traction to the limb. This action overcomes the powerful spasms of the quadriceps and hamstrings. These muscles pull bone fragments into a painful override that can cause massive internal bleeding.
- Step 3: Secure Straps. Position the splint under the injured leg. Secure the proximal ischial strap firmly against the pelvic bone. Attach the distal ankle hitch; ensure it's snug but doesn't cut off circulation.
- Step 4: Mechanical Traction. Engage the mechanical tensioning device. Gradually increase the pull until the injured leg is about the length of the uninjured leg, using about 10% of body weight and no more than about 15 lb (7 kg) (Merck Manual Professional, 2025).
- Step 5: Final Security and Re-assessment. Secure the remaining support straps to prevent lateral movement. Re-check PMS immediately. If pulses are lost, ease the tension slightly and reassess the limb's position.
Achieving the Correct Amount of Tension
Precision in tensioning prevents secondary trauma. Use the standard rule of thumb: apply traction equal to about 10% of the patient’s total body weight. Do not exceed about 15 lb (7 kg) of force (Merck Manual Professional, 2025; BCEHS protocol PR50). For open femur fractures, the BCEHS protocol uses 5 lb (2.5 kg) regardless of body weight. The primary goal is the relief of muscle spasms and the restoration of limb length. Don't over-pull. Traction splints can cause vascular or nerve traction injuries (Merck Manual Professional, 2025), and prolonged use can cause pressure sores (Davis et al., StatPearls, 2023). Monitor the patient’s face; the reduction of pain is your most reliable indicator of success.
Managing the Splint During Transport
The mission doesn't end once the traction splint is on. During tactical evacuation, equipment can shift. Re-check the ankle hitch and ischial strap frequently and after any significant patient movement. Ensure the splint’s frame doesn't interfere with litter straps or prevent the closure of aircraft or vehicle doors. Document the exact time of application and any changes in distal perfusion on the TCCC casualty card. Detailed logging ensures the receiving surgical team understands the patient's vascular history.
Training and Equipment Readiness for the Tactical Medic
High-end hardware fails in the hands of an untrained operator. A traction splint isn't a "plug and play" device; it's a precision tool that requires muscle memory developed through repetition. Train so you can perform the skill under high cognitive load. You can't afford to read instructions for the first time while your patient is in hypovolemic shock. Discipline in training ensures that when the adrenaline spikes, your hands move with clinical precision.
Conduct kit audits every 30 days without exception. Nylon straps degrade when exposed to UV radiation or extreme temperatures. Check the tensioning mechanisms on your traction splint to ensure they haven't seized or become clogged with debris. If a component shows fraying or structural cracks, replace it immediately. Reliability is the only metric that matters when you're 20 miles from the nearest Level 1 trauma center.
- Standardize your loadout: Ensure every team member uses the same model to allow for cross-compatibility.
- Force-on-force drills: Practice application while wearing full kit and gas masks.
- Environmental stress: Train in low-light and cold-weather environments to identify gear limitations.
Integrating Splints into Your IFAK or Medic Bag
Space is a premium in a standard IFAK. Fold your compact splints to fit the internal dimensions of your medic bag's secondary compartment. Place them behind the MARCH-specific modules for rapid access during the "Tactical Field Care" phase. Standardized components allow for faster turnover during a MIST report. In improvised scenarios, splint rods can serve as structural support for litters or temporary limb stabilization. Choosing battle-proven, standardized components over custom medical kits ensures that any medic on the stack can use your gear effectively.
Next Steps: Certification and Procurement
Mastery comes from veteran-led instruction by instructors with real operational experience. They teach you how to handle complications that technical manuals ignore, such as applying a traction splint on a patient with multiple limb injuries. Practice doesn't make perfect; perfect practice makes permanent. Enroll in a TCCC training course to bridge the gap between theory and survival. Once your skills are sharp, equip your team with the best traction splints and medical gear to ensure mission success and operator survival.
Secure the Fracture and Maintain the Mission
Managing a mid-shaft femur fracture in high-threat environments demands more than basic medical knowledge; it requires disciplined adherence to TCCC protocols. A properly deployed traction splint stabilizes the fracture site and is intended to reduce pain, bleeding, and further injury during long-range transport. You've learned that selecting a compact, tactical-grade device is essential for maintaining operator mobility without sacrificing clinical efficacy. Every second counts when a patient's femur is displaced. MED-TAC is a clinician-founded, veteran-led, SDVOSB-certified resource for professionals who prioritize mission success over marketing fluff. Our gear is battle-proven and built to function under extreme physiological stress. Don't let equipment failure or lack of training dictate the outcome of a life-saving intervention. Equip yourself with hardware designed for the rigors of the field.
Browse Field-Proven Traction Splints at MED-TAC
Your commitment to mastering these interventions saves lives. Stay focused, stay prepared, and keep your skills sharp for the next mission.
Frequently Asked Questions
Can I apply a traction splint if the patient has a suspected pelvic fracture?
No, you shouldn't apply a traction splint if a pelvic fracture is suspected. The pelvis serves as the anchor point for the splint, and pelvic fracture is a listed contraindication (Merck Manual Professional, 2025). TCCC Guidelines call for a pelvic binder for suspected pelvic fracture after severe blunt force or blast injury with pelvic pain, a major lower limb amputation or near amputation, exam findings suggesting pelvic fracture, unconsciousness, or shock (TCCC Guidelines, 01 May 2026).
How much traction should I apply to a fractured femur?
Apply traction equal to about 10% of the patient's body weight, not to exceed about 15 pounds (7 kg) (Merck Manual Professional, 2025). The goal is to stabilize the fracture and reduce muscle spasms that cause bone fragments to overlap. Stop tensioning once the injured limb's length matches the unaffected side or when the patient experiences a reduction in pain. Over-tensioning risks neurovascular compromise.
What is the difference between a unipolar and bipolar traction splint?
The primary difference lies in the frame design; a unipolar splint uses a single rod while a bipolar splint uses two. Unipolar devices like the Sager are placed along the medial aspect of the leg, and some unipolar designs can splint both legs. Bipolar devices like the Hare splint provide a more rigid external frame but are generally heavier and bulkier than compact unipolar models.
Is a traction splint used for open (compound) femur fractures?
Yes. Traction splints are used for both closed and open mid-shaft femur fractures (Davis et al., StatPearls, 2023). Control bleeding and dress the wound first. Some EMS protocols reduce traction for open fractures; BCEHS protocol PR50 uses 5 lb (2.5 kg) regardless of body weight.
How long can a traction splint remain on a patient during evacuation?
A traction splint is a temporary device. Remove it as soon as definitive care is available (Merck Manual Professional, 2025), because prolonged use can cause pressure sores (Davis et al., StatPearls, 2023). Recheck distal neurovascular status repeatedly to ensure the ankle hitch hasn't compromised distal blood flow. If you're operating in a prolonged field care environment, reassess the tension after any significant temperature change or altitude shift during air transport.
Can one person apply a Slishman Traction Splint (STS) alone?
The manufacturer states the Slishman Traction Splint (STS) can be applied in under 60 seconds with minimal training, and traction is set at the hip rather than pulled from the foot. A single trained operator can apply it, but a second set of hands to hold manual traction still makes application easier when available.
What happens if I over-tighten the traction on a patient?
Over-tightening the device can cause vascular or nerve traction injury (Merck Manual Professional, 2025) and, over time, pressure sores. Keep traction at or below about 15 lb (7 kg). Watch for the 5 Ps: pain, pallor, pulselessness, paresthesia, and paralysis. If distal pulses disappear, you must immediately reduce the tension until the pulse returns.
Are traction splints included in a standard IFAK?
No, traction splints are not part of a standard Individual First Aid Kit (IFAK). They're specialized tools usually found in vehicle-based trauma kits or a medic's aid bag. Some kits carry a malleable splint such as a SAM Splint for general immobilization, but the components required for femoral traction are too bulky for a standard belt-mounted pouch.
Leave a comment